
Our Hospital RCM services help healthcare organizations optimize revenue through accurate coding, claims management, compliance support, and denial prevention. We streamline complex hospital billing workflows to improve reimbursements, reduce revenue leakage, and support long-term financial performance.

At its core, eligibility verification confirms that a patient’s UnitedHealthcare coverage is active and applies to the specific service being planned. It’s a step that carries far more weight than a quick “yes, they’re covered” glance.
This section distinguishes eligibility from benefits verification, clarifies how it relates to — but isn’t the same as — prior authorization, and situates the entire check within the larger revenue cycle so your team knows exactly why it matters.
Confirming UnitedHealthcare coverage before a visit takes place is one of the simplest ways to head off avoidable denials and last-minute billing surprises. It also gives your team a clear window to identify what the patient will owe.
Beyond denial prevention, upfront verification reduces the amount of rework your front desk and billing staff face later, and it directly protects the practice’s cash flow by catching issues before services are rendered rather than after.
Reliable verification results depend entirely on accurate patient information gathered at the front desk. A single transposed digit in a member ID can derail the entire process.
Staff should consistently record the patient’s full name and demographics, date of birth, member/subscriber ID, group number, insurance card details, subscriber relationship, both primary and secondary coverage where relevant, and the planned date and type of service.
With intake complete, the next step is validating a specific set of facts with UnitedHealthcare itself — not just whether the plan is active, but the terms under which it operates.
This includes active/inactive status, effective and termination dates, plan/product type, provider network status, covered benefits, deductible and deductible remaining, copayment, coinsurance, out-of-pocket maximum, benefit limitations, exclusions, referral requirements, prior authorization needs, and coordination of benefits. Similar to what Aetna reports through its electronic eligibility responses — active coverage, effective/termination dates, deductibles, copays, coinsurance, plan limits, and COB data — UnitedHealthcare’s electronic responses generally follow the same structure.
Use our UnitedHealthcare eligibility verification checklist to confirm active coverage, effective dates, plan type, network status, benefits, deductibles, copays, coinsurance, and service-specific requirements before care is provided. We help you verify these details upfront so you can identify coverage issues early, reduce avoidable denials, and improve billing and reimbursement accuracy.
| Verification Item | What to Check | Why It Matters | Action Required |
|---|---|---|---|
| Coverage status | Active/inactive on date of service | Confirms service will be payable | Verify before every visit |
| Effective/termination dates | Start and end of coverage | Prevents lapsed-coverage denials | Cross-check against DOS |
| Plan/product type | HMO, PPO, EPO, POS | Determines network and referral rules | Identify exact plan name |
| Network status | In-network vs. out-of-network | Impacts reimbursement and patient cost | Confirm provider and facility |
| Deductible | Individual/family, met/remaining | Affects patient responsibility | Document current balance |
| Copay/coinsurance | Amount by service type | Needed for accurate patient estimate | Confirm per CPT category |
| Benefit limitations | Visit caps, exclusions | Avoids non-covered service denials | Match against planned service |
| Authorization/referral | Required or not | Prevents authorization-related denials | Confirm before scheduling |
| COB status | Primary/secondary payer order | Prevents COB-related denials | Verify with both payers |
Working through a fixed sequence every time removes guesswork and ensures thoroughness, no matter which staff member is handling the check.
The recommended flow: collect accurate patient information, validate the member ID, confirm coverage for the date of service, identify the exact plan, confirm network participation, verify service-specific benefits, review cost-sharing, check authorization or referral requirements, verify COB, and document the result.
Electronic eligibility checks rely on a standardized HIPAA transaction pair — the 270 inquiry sent by the provider and the 271 response returned by the payer — and understanding this exchange helps your team interpret results with confidence.
The 271 response typically returns coverage status, effective dates, benefit details, and cost-sharing figures through your clearinghouse or practice-management system. For Medicare Fee-for-Service, CMS’s HETS system accepts HIPAA-compliant 270 inquiries and returns real-time 271 responses — a useful reference point for how commercial payers like UnitedHealthcare structure their own electronic exchanges.
We compare UnitedHealthcare eligibility verification methods so you can understand how each option supports coverage, benefit, network, and patient responsibility checks before service. You can use this comparison to select the right verification channel, improve response accuracy, reduce manual follow-up, and prevent eligibility-related claim issues.
| Verification Method | Best Use | Information Available | Advantages | Potential Limitations |
|---|---|---|---|---|
| Payer portal | Routine daily checks | Coverage, benefits, plan details | Fast, self-service | Portal downtime, incomplete data |
| 270/271 transaction | High-volume automated checks | Standardized coverage/benefit data | Real-time, scalable | May lack plan-specific nuance |
| Clearinghouse | Batch or integrated workflows | Aggregated payer responses | Works across multiple payers | Dependent on clearinghouse accuracy |
| Phone verification | Complex or unclear cases | Representative-confirmed details | Personalized answers | Time-consuming, hold times |
| Automated verification | Recurring/scheduled patients | Standard eligibility fields | Reduces manual workload | Limited for complex benefits |
| Manual payer rep verification | High-cost or ambiguous services | Detailed, case-specific answers | Highest accuracy for edge cases | Slowest, resource-intensive |
Correctly reading an eligibility response is just as important as running the check itself — a response can appear straightforward while still hiding details that change the billing outcome entirely.
Review coverage status, plan name, effective dates, service type, deductible figures, copay and coinsurance, out-of-pocket totals, network indicators, benefit limitations, and any authorization or referral flags before concluding a service is fully covered.
One of the most common and expensive misconceptions is assuming that “active” coverage means a service will automatically be paid. UnitedHealthcare, like most payers, applies exclusions, frequency limits, and medical necessity rules that don’t show up in a basic status check.
Before assuming payment, confirm benefit maximums, network restrictions, and whether prior authorization applies to the specific procedure or specialty being billed.
We help you identify frequent UnitedHealthcare eligibility problems, including inactive coverage, member-data mismatches, plan changes, network discrepancies, and incomplete benefit information. You can address these issues before service by validating eligibility responses and confirming unclear coverage details, helping reduce denials, rework, and reimbursement delays.
| Eligibility Problem | What It Means | Claim/Revenue Risk | Recommended Solution |
|---|---|---|---|
| Inactive coverage | Policy terminated or not yet active | Denied claim | Reverify before scheduling |
| Incorrect member ID | Wrong or mistyped ID number | Rejected eligibility request | Confirm against insurance card |
| Wrong payer identified | Patient has a different plan | Claim sent to wrong payer | Re-verify payer and plan |
| Coverage terminated | Policy ended before DOS | Full claim denial | Check termination date pre-visit |
| Provider out of network | No network agreement | Reduced or denied reimbursement | Confirm network status in advance |
| Incorrect COB | Wrong primary/secondary order | Delayed or denied payment | Verify COB with both payers |
| Missing authorization | Required auth not obtained | Authorization denial | Confirm auth requirement early |
| Benefit exclusion | Service not covered under plan | Non-covered denial | Check service-specific benefits |
| Deductible not met | Patient owes full/partial cost | Unexpected patient balance | Communicate estimate pre-visit |
| Incorrect plan selected | Wrong product type on file | Claim processing errors | Confirm exact plan name |
Getting cost-sharing figures right is central to setting accurate patient expectations, and mistakes here create friction at check-out and downstream in collections. Individual and family deductibles often differ, so confirming which one applies is essential.
Your team should also distinguish deductible met from deductible remaining, understand copay by service category, know applicable coinsurance percentages, and factor in how in-network versus out-of-network status changes the final estimate shared with the patient.
We help you verify UnitedHealthcare patient financial responsibility by confirming deductibles, copays, coinsurance, out-of-pocket balances, and applicable benefit limitations before services are provided. You can use these verified details to communicate expected costs clearly, improve upfront collections, and reduce patient billing disputes.
| Cost-Sharing Element | What to Verify | Example Scenario | Why Providers Need It |
|---|---|---|---|
| Deductible | Amount met vs. remaining | $500 remaining before coverage kicks in | Sets accurate patient estimate |
| Copay | Fixed amount per visit type | $30 for specialist visit | Collected at time of service |
| Coinsurance | Percentage owed after deductible | 20% coinsurance on imaging | Impacts high-cost service estimates |
| Out-of-pocket max | Remaining limit for the year | $200 left before max is reached | Determines when costs stop |
| Network status | In vs. out-of-network cost difference | Higher coinsurance out-of-network | Prevents billing surprises |
Network participation isn’t always consistent within a provider group — a facility might be in-network while a specific rendering provider is not. UnitedHealthcare’s range of plan-specific networks makes this distinction worth checking every time.
Confirm participation at the provider, facility, and location level, and check whether the specific plan includes referral or network restrictions that could affect reimbursement.
Different plan structures come with different rules around referrals, networks, and authorization, so pinpointing the exact plan — not just the payer name — is critical to getting verification right.
Common types to distinguish include HMO, PPO, EPO, POS, Medicare, Medicare Advantage, Medicaid, Managed Medicaid, employer-sponsored plans, and Marketplace/Exchange products, each carrying UnitedHealthcare-specific variations.
We help you verify the patient’s UnitedHealthcare plan type and its specific network, referral, benefit, and authorization requirements before services are provided. You can confirm these details upfront to follow the correct billing pathway, identify coverage restrictions, and prevent avoidable eligibility-related denials.
| Plan Type | Network Requirement | Referral Risk | Authorization Consideration | Verification Priority |
|---|---|---|---|---|
| HMO | Strict in-network only | High | Often required | Critical |
| PPO | Flexible, in/out-of-network | Low | Sometimes required | High |
| EPO | In-network only, no referrals | Low | Sometimes required | High |
| POS | Hybrid, referral-dependent | Medium | Sometimes required | Medium |
| Medicare Advantage | Plan-specific network | Medium | Often required | Critical |
| Managed Medicaid | Strict network | High | Often required | Critical |
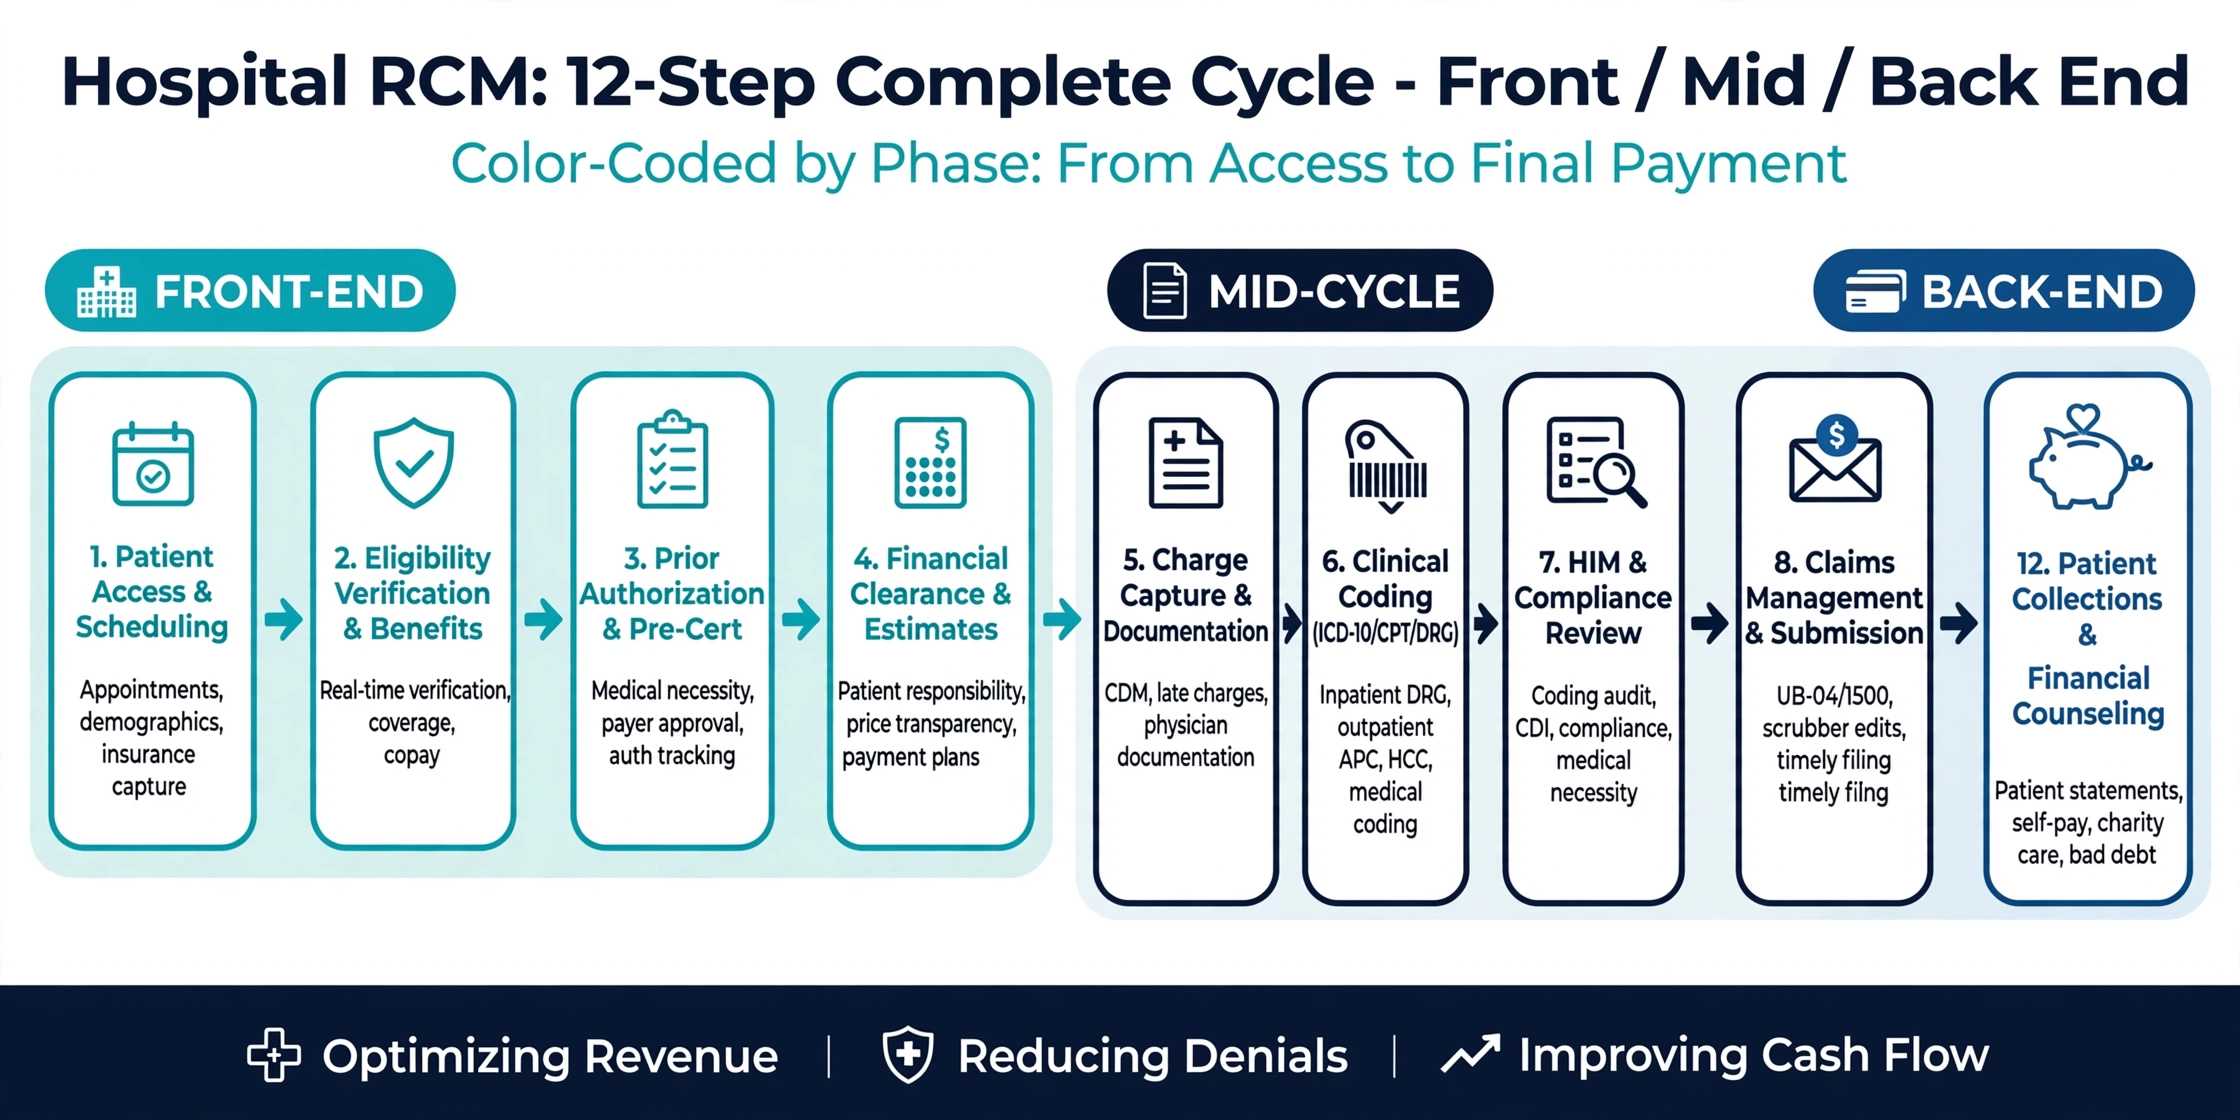
Authorization requirements are easy to overlook when they’re treated as a separate task from eligibility, and combining the two into one workflow significantly reduces the risk of delivering a service that’s later denied for lack of approval.
During verification, identify which services require authorization, confirm responsibility for obtaining it, note effective dates, approved units or visits, and flag anything unclear for follow-up ahead of the appointment.
Referral rules shift depending on plan type and specialty, and an expired or missing referral can trigger a denial even when the underlying coverage is fully active.
Confirm whether a PCP or specialist referral applies, HMO-specific requirements, referral validity dates, the number of approved visits, and any restrictions tied to the rendering provider.
When a patient carries more than one insurance plan, determining payer order correctly avoids unnecessary processing delays. Outdated COB records remain a frequent, avoidable source of denials.
Confirm primary versus secondary status, watch for Medicare secondary payer scenarios, account for multiple commercial plans or Medicaid as secondary, and understand how patient responsibility shifts when COB information is wrong.
We help you verify whether UnitedHealthcare is the patient’s primary or secondary coverage by confirming other active insurance, coordination of benefits, coverage dates, and payer sequencing requirements. You can establish the correct billing order before claim submission to prevent COB-related denials, incorrect patient balances, and reimbursement delays.
| Scenario | Likely Verification Issue | What Staff Should Confirm | Recommended Action |
|---|---|---|---|
| Two commercial plans | Unclear primary/secondary order | Birthday rule or employer coverage | Confirm order with both payers |
| Medicare + commercial | Medicare secondary payer rules | Which plan pays first | Apply MSP questionnaire |
| Medicaid as secondary | Medicaid always pays last | Primary payer processed first | Bill primary before Medicaid |
| Outdated COB on file | Old insurance still listed as primary | Current active coverage | Update COB before billing |
Coverage rules often vary by service line, so a general eligibility check isn’t sufficient for specialties with their own unique benefit structures. Each service category deserves its own dedicated verification.
This spans office visits, specialist visits, behavioral health, physical therapy, occupational therapy, speech therapy, ABA therapy, diagnostic imaging, laboratory services, surgery, DME, home health, and telehealth — each carrying distinct authorization, frequency, and network considerations under UnitedHealthcare plans.
We help you verify UnitedHealthcare benefits by service category, including coverage levels, visit or frequency limits, cost-sharing, network requirements, and prior authorization conditions. You can confirm these details before care to identify benefit restrictions early, estimate patient responsibility accurately, and reduce service-specific claim denials.
| Service Category | Benefits to Verify | Common Limitation | Authorization/Referral Check | Provider Risk |
|---|---|---|---|---|
| Behavioral health | Session limits, copay | Visit caps per year | Often required | Denial if cap exceeded |
| Physical therapy | Visit limits, coinsurance | Frequency limits | Often required | Non-covered visits |
| Diagnostic imaging | Coverage, network | Pre-cert for advanced imaging | Frequently required | Authorization denial |
| DME | Coverage, rental vs. purchase | Quantity limits | Often required | Non-covered equipment |
| Telehealth | Covered modality, copay | Platform/provider restrictions | Sometimes required | Reimbursement reduction |
Even seasoned staff tend to repeat certain patterns that lead directly to denials. Recognizing them is the first step toward eliminating them.
Frequent missteps include verifying too early, failing to reverify closer to the date of service, checking only active/inactive status, overlooking service-specific benefits, missing plan changes, entering incorrect demographics, skipping network checks, missing COB updates, failing to document verification, and assuming authorization is confirmed simply because coverage is active.
We help you identify UnitedHealthcare verification errors that can lead to eligibility denials, incorrect patient responsibility, non-covered services, claim rework, and delayed reimbursement. You can catch these issues before care is provided to protect revenue, reduce avoidable A/R, and maintain a more consistent billing workflow.
| Staff Error | Possible Consequence | Revenue-Cycle Impact | Prevention Strategy |
|---|---|---|---|
| Checked too early | Coverage changes before DOS | Late-stage denial | Reverify closer to visit |
| Only checked active status | Missed exclusions | Non-covered denial | Full benefit verification |
| Incorrect demographics | Rejected eligibility request | Processing delay | Cross-check insurance card |
| Missed authorization | Service delivered without approval | Authorization denial | Confirm auth during verification |
| No documentation | No record of what was verified | Difficulty appealing denials | Standardized documentation log |
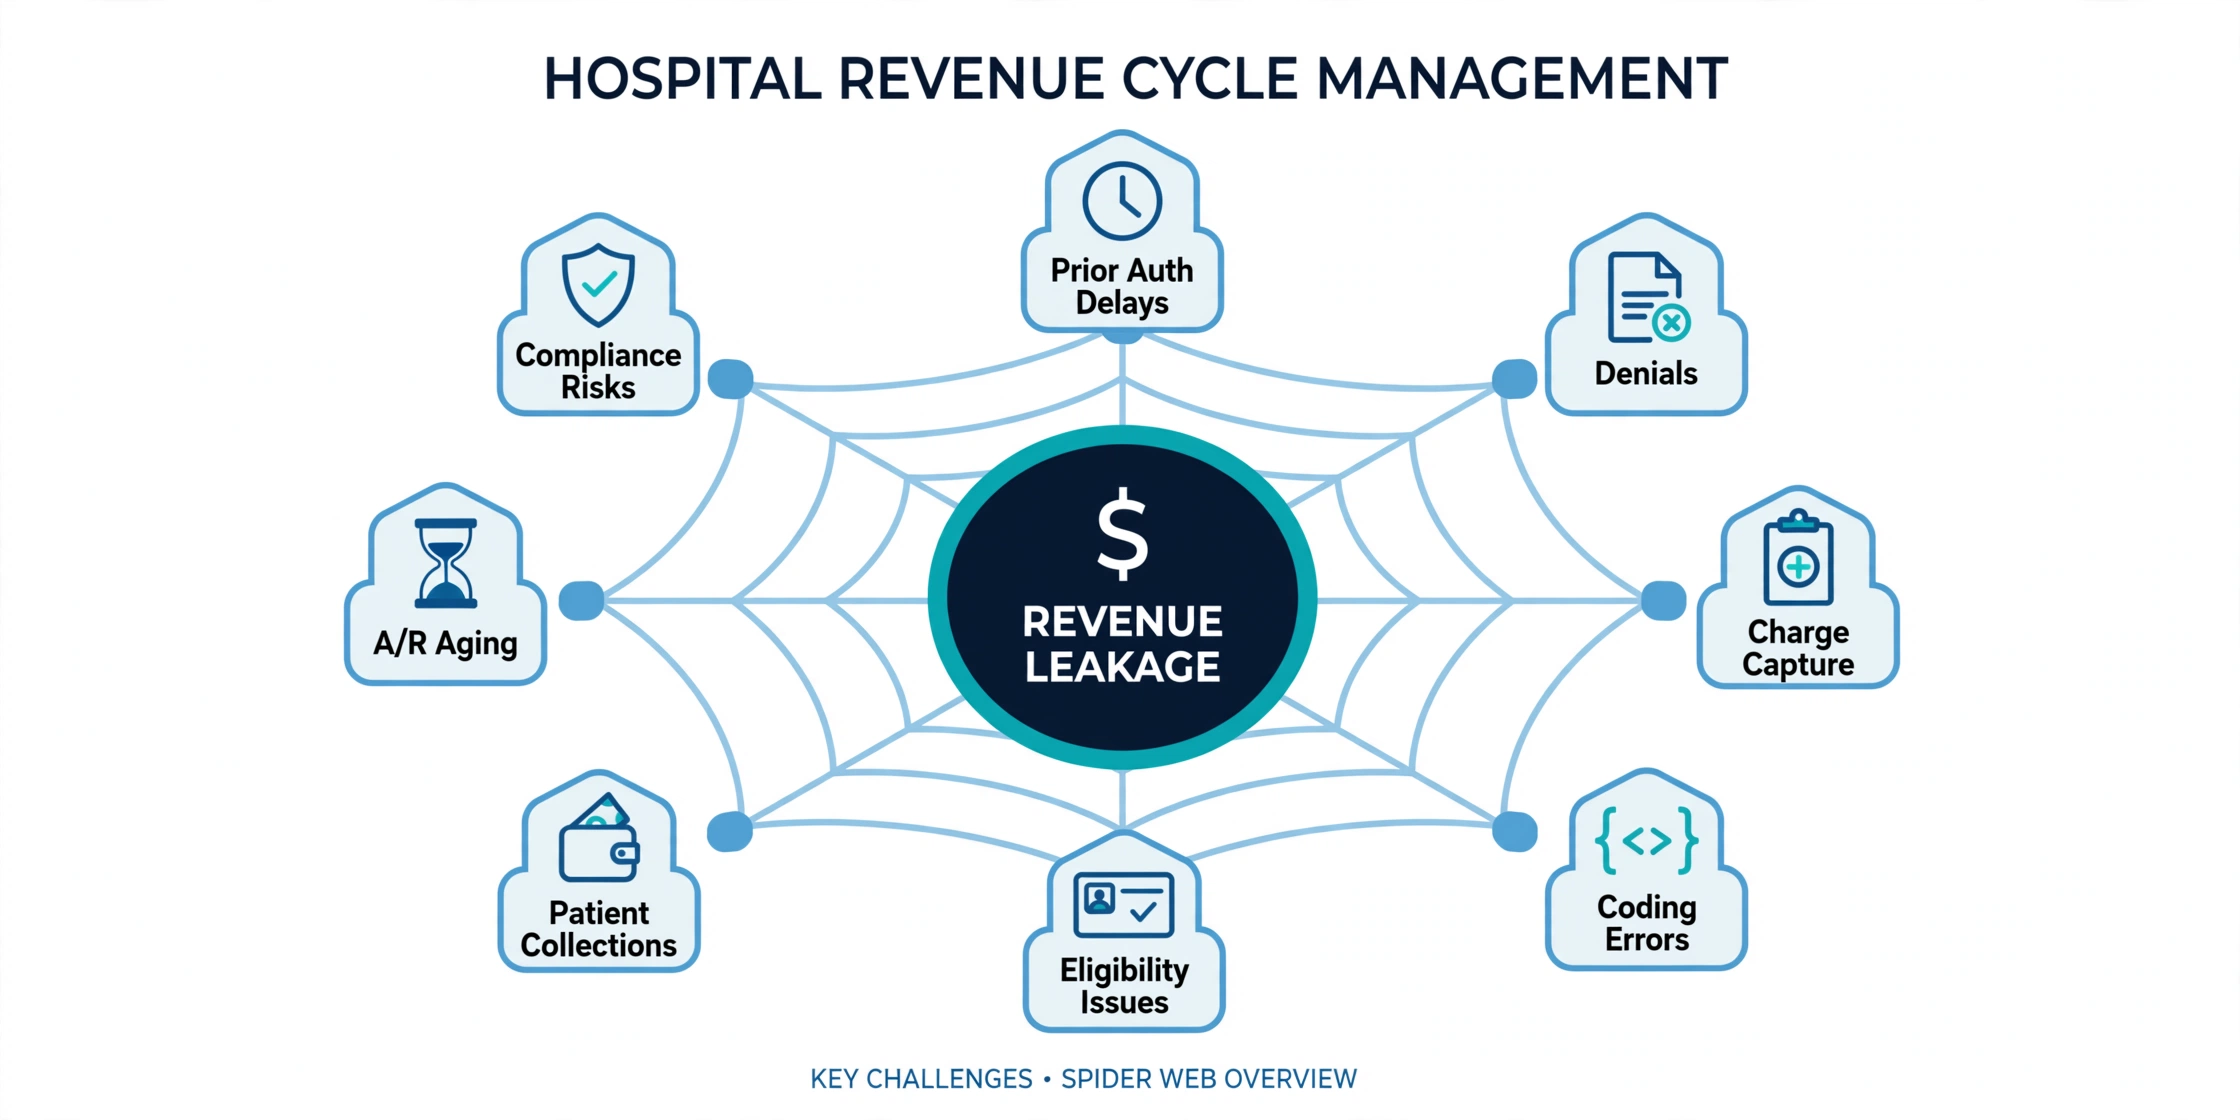
First-time and returning patients call for slightly different approaches — new patients need a full benefit workup, while returning patients need a targeted check for anything that’s changed since their last visit.
Key triggers for returning patients include insurance changes, the start of a new benefit year, new employer coverage, adjusted deductibles or benefits, and updated insurance cards.
Because coverage can shift between scheduling and the actual appointment, establishing defined reverification checkpoints keeps your eligibility data reliable.
Recommended checkpoints include at scheduling, shortly before the appointment, on the date of service, after any known insurance change, at the start of a new benefit year, and before high-cost or recurring treatments.
We help you build a practical UnitedHealthcare verification timeline that starts at scheduling, continues with detailed benefit checks before service, and includes final eligibility confirmation close to the date of care. You can use this workflow to catch coverage or plan changes early, prevent last-minute issues, and reduce eligibility-related claim denials.
| Verification Stage | Timing | What to Check | Staff Action | Risk Prevented |
|---|---|---|---|---|
| At scheduling | Initial contact | Basic eligibility | Confirm coverage exists | Wasted scheduling effort |
| Before appointment | 24–72 hours prior | Full benefits | Detailed verification | Day-of surprises |
| Date of service | Day of visit | Real-time status | Final confirmation | Coverage lapses |
| After insurance change | As reported | Updated plan details | Full reverification | Claim mismatches |
| New benefit year | January or plan renewal | Reset deductibles/limits | Annual re-check | Outdated benefit assumptions |
High-cost services carry greater financial exposure when verification is incomplete, which makes a more detailed review worthwhile ahead of scheduling.
For these cases, confirm detailed benefits, authorization status, network participation, benefit maximums, deductible and coinsurance exposure, and prepare a clear financial estimate for the patient backed by documented reference numbers.
Many of the most common denial categories can be traced directly back to gaps in front-end verification, making this one of the highest-leverage areas for reducing denials overall.
Verification helps prevent denials tied to inactive coverage, non-covered services, COB mismatches, missing authorization, network issues, incorrect patient information, and plan mismatches — all before a claim is ever submitted.
We help you identify common UnitedHealthcare denial scenarios, including inactive coverage, network mismatches, missing authorizations, benefit limitations, and coordination-of-benefits issues. You can apply the right verification action before service to correct these risks early, reduce preventable denials, and avoid unnecessary claim rework.
| Denial Scenario | Root Cause | What Should Have Been Verified | Corrective Action | Preventive Action |
|---|---|---|---|---|
| Inactive coverage denial | Coverage lapsed before DOS | Effective/termination dates | Appeal with updated info | Reverify closer to DOS |
| Non-covered service | Service excluded from plan | Benefit details | Adjust billing or appeal | Verify service-specific benefits |
| COB denial | Wrong payer billed first | Primary/secondary order | Rebill correct payer order | Confirm COB each visit |
| Authorization denial | No prior approval obtained | Authorization requirement | Retroactive auth request | Confirm auth before service |
A verification isn’t truly complete until it’s documented in a way that holds up if it’s ever needed for an appeal or audit.
Solid documentation includes the date and time of verification, method used, representative name if applicable, reference number, coverage dates, confirmed benefits, patient responsibility, authorization or referral details, and any electronic response records or staff notes.
When the payer portal doesn’t align with what the patient reports, resolving the discrepancy before billing helps avoid unnecessary denials.
Steps include rechecking demographics, validating the insurance card, contacting the payer directly, asking the patient about recent coverage changes, checking for an alternate payer or plan, documenting the conflict, and holding nonurgent billing actions until it’s resolved.
Medicare-affiliated coverage brings its own verification nuances, particularly around UnitedHealthcare’s Medicare Advantage offerings.
Key areas include understanding Part A and Part B interactions, verifying Medicare Advantage details directly with UnitedHealthcare, using HETS for FFS 270/271 checks, confirming Medicare entitlement dates, and applying Medicare secondary payer rules where applicable. CMS specifies that HETS applies to Medicare Fee-for-Service eligibility only, and that Medicare Advantage eligibility should be verified with the applicable plan directly — meaning UnitedHealthcare Medicare Advantage members require verification through UnitedHealthcare’s own systems.
Medicaid verification is inherently state-specific, and UnitedHealthcare’s Community Plan products vary by state program, so a uniform national workflow rarely applies cleanly.
Your process should account for differences between Medicaid and Managed Medicaid, use the applicable state Medicaid portal, confirm eligibility effective dates, identify plan assignment and managed care organization, and adjust reverification frequency to match state-specific requirements.
While the core verification steps remain consistent, each commercial payer has its own portal behavior, response format, and network structure worth understanding on its own terms.
This section can be expanded with payer-specific subsections for UnitedHealthcare, Cigna, Aetna, Blue Cross Blue Shield, Humana, Kaiser Permanente, Molina Healthcare, Centene plans, Anthem/Elevance, and other regional payers relevant to your practice.
We compare Medicare, Medicaid, and commercial insurance verification so you can understand how eligibility rules, benefit structures, network requirements, cost-sharing, and payer processes differ. You can use these differences to apply the correct verification workflow for each coverage type, improve billing accuracy, and reduce preventable claim denials.
| Area | Medicare | Medicaid | Commercial Insurance | Key Provider Consideration |
|---|---|---|---|---|
| Verification method | HETS 270/271 | State portal | Payer portal/270-271 | Different systems per payer type |
| Network rules | FFS: none; MA: plan-specific | State/MCO-specific | Plan-specific | Confirm MA/MCO separately |
| Reverification frequency | Annually / per event | Frequent, state-dependent | Per benefit year | Build payer-specific cadence |
| Authorization complexity | Moderate | Often high | Varies by plan | Track per payer |
A clearly mapped workflow keeps every team member aligned on responsibilities and timing, reducing the chance of gaps between scheduling and service delivery.
A typical flow looks like: Patient Scheduled → Insurance Information Collected → Eligibility Checked → Benefits Verified → Network Confirmed → Authorization/Referral Checked → Patient Responsibility Identified → Verification Documented → Patient Informed.
We help you define who is responsible for each UnitedHealthcare verification step, from checking eligibility and plan details to confirming benefits, network status, authorization, and patient responsibility. You can use this matrix to establish clear ownership, prevent missed verification tasks, and maintain a consistent pre-service workflow.
| Task | Front Desk | Eligibility Team | Billing Team | Authorization Team | When Completed |
|---|---|---|---|---|---|
| Collect patient info | ✔ | At scheduling | |||
| Verify active coverage | ✔ | Before appointment | |||
| Confirm benefits | ✔ | Before appointment | |||
| Check authorization | ✔ | Before service | |||
| Document verification | ✔ | ✔ | Throughout process |
When eligibility verification is done thoroughly, patients experience fewer billing surprises and gain a clearer picture of what to expect financially — which builds confidence in the practice.
Benefits include fewer unexpected bills, greater financial transparency, earlier identification of coverage problems, clearer communication of patient responsibility, and smoother interactions on the day of the appointment.
We help you improve UnitedHealthcare eligibility verification to reduce preventable denials, minimize claim rework, strengthen upfront collections, and avoid delays caused by incorrect coverage information. You can turn accurate pre-service verification into cleaner claims, lower administrative costs, faster reimbursement, and more predictable revenue.
| Benefit | Operational Impact | Financial Impact | Patient Impact |
|---|---|---|---|
| Fewer denials | Less rework for billing team | Faster reimbursement | Fewer billing disputes |
| Accurate estimates | Smoother check-out process | Higher point-of-service collections | Reduced billing surprises |
| Documented verification | Easier appeals process | Recovered revenue on disputed claims | Increased trust in practice |
Maintaining consistent quality control keeps eligibility verification accurate as patient volume and payer complexity continue to grow.
Core components include daily verification queues, unverified-patient reports, exception management, periodic verification and documentation audits, denial feedback loops, ongoing staff training, and regularly updated payer-specific SOPs.
Tracking the right indicators helps practices pinpoint where verification breakdowns occur and measure improvement over time.
Metrics worth monitoring include the percentage of scheduled patients verified, verification completion rate before the date of service, eligibility-related and COB-related denial rates, registration error rate, authorization-related front-end issues, turnaround time, and unverified account volume.
We help you track UnitedHealthcare eligibility verification KPIs such as verification completion, response accuracy, turnaround time, unresolved coverage issues, and eligibility-related denials. You can use these metrics to identify workflow gaps, measure verification performance, and improve the financial efficiency of your pre-service process.
| KPI | What It Measures | Why It Matters | Improvement Action |
|---|---|---|---|
| % patients verified | Coverage of verification process | Identifies gaps in workflow | Expand verification queue capacity |
| Denial rate (eligibility) | Front-end verification accuracy | Direct revenue impact | Targeted staff retraining |
| Verification turnaround | Speed of process completion | Impacts scheduling efficiency | Automate routine checks |
| Unverified account volume | Backlog size | Signals resource strain | Reassign or outsource overflow |
As patient volume and payer complexity increase, many practices reach a point where in-house verification alone can’t keep pace with demand.
Common triggers include high patient volume, limited front-desk staffing, rising eligibility-related denials, multiple payer contracts, multi-location operations, specialty-specific benefit complexity, staff turnover, and a growing verification backlog.
Deciding between in-house and outsourced verification comes down to staffing capacity, payer expertise, and how consistently your practice can maintain the workflow internally.
Key comparison points include staffing and training requirements, depth of payer expertise, scalability during volume spikes, quality control processes, workflow consistency, overall cost, and coverage continuity during staff absences.
We compare in-house and outsourced UnitedHealthcare eligibility verification so you can evaluate staffing needs, verification accuracy, turnaround time, payer follow-up, and administrative workload. You can choose the right approach to streamline pre-service checks, reduce eligibility-related denials, and improve overall revenue cycle efficiency.
| Area | In-House Team | Outsourced Team | Provider Consideration |
|---|---|---|---|
| Staffing | Requires hiring/training | Ready-made expertise | Faster ramp-up with outsourcing |
| Payer expertise | Limited to internal experience | Broad, multi-payer experience | Fewer errors on complex plans |
| Scalability | Constrained by headcount | Flexible capacity | Easier to handle volume swings |
| Cost | Fixed salary/benefits cost | Variable, usage-based cost | Depends on practice size |
| Coverage during absence | Gaps during turnover/leave | Continuous coverage | Reduces backlog risk |
House of Outsourcing delivers end-to-end eligibility and benefits verification tailored to payer-specific workflows, including UnitedHealthcare’s plan structures and documentation standards.
Our support spans Medicare and Medicaid verification, commercial payer checks, patient responsibility confirmation, network status review, authorization and referral identification, COB verification, and thorough documentation that integrates directly with your existing billing workflows.
House of Outsourcing brings over fifteen years of hands-on experience in eligibility and revenue cycle operations across a wide range of specialties and payer types.
Our team understands payer-specific workflows in depth, manages complex benefit verification with precision, and supports front-end revenue-cycle operations through quality-focused, scalable processes built for growing healthcare organizations.
Practices choose House of Outsourcing because our verification team pairs payer-specific expertise with consistent documentation standards and a genuine focus on preventing denials before they occur.
We take administrative workload off internal staff, support broader revenue-cycle goals, and scale alongside your organization as patient volume and payer complexity increase.
Before every appointment, confirm: Is coverage active? Is it valid for the date of service? Is the provider in-network? Is the requested service covered? What is the deductible, copay, and coinsurance? What out-of-pocket amount remains?
Also confirm: Is prior authorization required? Is a referral needed? Are there benefit limits? Is COB accurate? And finally, has the entire verification been properly documented?
UnitedHealthcare eligibility can be verified through the payer portal, a 270/271 electronic transaction, a clearinghouse, or by phone with a representative, depending on the complexity of the case.
At minimum, at scheduling and again shortly before the date of service, with additional checks after any known insurance change or at the start of a new benefit year.
Patient demographics, subscriber ID, group number, insurance card details, and the planned date and type of service.
No, active coverage doesn’t guarantee that a specific service is covered, so benefit-level details must also be verified.
Through the payer portal, electronic eligibility response, or direct confirmation with a UnitedHealthcare representative.
Authorization requirements should be confirmed as part of the same verification process, using the payer portal or by contacting UnitedHealthcare directly.
Nonurgent services should be held until the discrepancy is resolved, and the conflict should be documented for follow-up.
Yes, returning patients should be reverified for any insurance, benefit, or demographic changes since their last visit.
By confirming primary versus secondary order with both payers and updating COB records accordingly.
Yes, many practices outsource eligibility verification to reduce administrative burden and improve accuracy at scale.
Get a free assessment from our billing experts
